All published articles of this journal are available on ScienceDirect.

Health Literacy Regarding Stroke Recognition and Emergency Medical Services Utilization Among Patients with Acute Stroke in Thailand: A Multicenter Cross-Sectional Study

Abstract
Introduction/Objective
Early stroke recognition and EMS activation reduce prehospital delay. This study assessed stroke-related health literacy and EMS utilization among patients with acute stroke in Thailand, as well as factors associated with timely hospital arrival (≤4.5 hours).
Methods
A multicenter cross-sectional study included 1,292 patients with acute stroke from four tertiary hospitals in Thailand. Structured interviews and medical-record review assessed stroke knowledge, perceived severity, EMS awareness, attitudes toward EMS utilization, and healthcare access. A generalized linear mixed model with hospital as a random effect was used to examine factors associated with timely arrival.
Results
Moderate stroke knowledge was observed among 600 participants (46.4%), moderate perceived severity among 500 (38.7%), and moderate EMS attitudes among 560 (43.3%). Awareness of the national EMS number (1669) was reported by 640 (49.5%), and 625 (48.4%) had previous EMS experience. Timely arrival occurred in 650 (50.3%). Significant factors were sudden symptom onset (aOR 2.50, 95% CI 1.85-3.35), moderate NIHSS severity (aOR 2.00, 95% CI 1.40-2.85), severe NIHSS severity (aOR 4.50, 95% CI 2.80-7.20), awareness of 1669 (aOR 1.70, 95% CI 1.30-2.20), caregiver assistance (aOR 3.75, 95% CI 2.79-5.05), and distance ≥35 km (aOR 4.10, 95% CI 3.00-5.60) (all p<0.001).
Discussion
Stroke-related health literacy was generally moderate, but gaps in EMS awareness remained. Timely arrival was associated with symptom characteristics, stroke severity, EMS awareness, caregiver support, and access factors.
Conclusion
Strengthening stroke-symptom recognition, EMS number awareness, caregiver preparedness, and access to emergency care may support earlier hospital arrival.
1. INTRODUCTION
Stroke is one of the leading causes of mortality and long-term disability worldwide, imposing a substantial burden on patients, families, and healthcare systems. According to the Global Burden of Disease (GBD) Study, stroke remains a major contributor to premature death and disability-adjusted life years (DALYs), particularly in low- and middle-income countries where access to timely treatment remains limited [1]. As populations continue to age and the prevalence of cardiovascular risk factors increases, the burden of stroke is expected to rise further, highlighting the need for effective strategies to improve early recognition and access to emergency care [2].
Timely recognition of stroke symptoms and prompt activation of emergency medical services (EMS) are critical determinants of successful stroke management. Acute ischemic stroke is a time-sensitive medical emergency in which rapid reperfusion therapy can significantly reduce mortality and disability [3]. International clinical guidelines emphasize that patients should seek immediate medical attention and activate EMS as soon as stroke symptoms occur [3, 4]. Delays in recognizing symptoms or contacting EMS may result in missed therapeutic opportunities and poorer clinical outcomes [5].
Health literacy has emerged as an important factor influencing health-related decision-making and healthcare utilization. Health literacy encompasses individuals' ability to access, understand, evaluate, and apply health information to make appropriate healthcare decisions [5, 6]. In the context of stroke, adequate health literacy enables individuals to recognize warning symptoms, understand the urgency of treatment, and appropriately utilize EMS services. Previous studies have demonstrated that limited health literacy is associated with delayed hospital arrival, lower EMS utilization, poor adherence to treatment recommendations, and worse health outcomes [7-11].
Recent evidence indicates that stroke-related health literacy remains suboptimal in many populations worldwide, particularly regarding recognition of stroke warning signs and awareness of emergency medical service activation. Insufficient stroke literacy may contribute to delays in seeking emergency care, resulting in missed opportunities for time-sensitive treatments and poorer clinical outcomes. Therefore, improving stroke-related health literacy has become an important public health strategy for enhancing timely access to acute stroke care and reducing stroke-related disability and mortality [12-14]. Recent systematic reviews and regional evidence continue to show that prehospital delay is influenced by stroke recognition, EMS use, distance, and health-system access, while disparities in acute stroke treatment persist across Asian settings [15-17].
In Thailand, stroke is a major public health problem and remains one of the leading causes of death and disability [12, 18, 19]. Despite ongoing national campaigns promoting stroke awareness and emergency medical service utilization through the universal emergency number (1669), delayed hospital arrival remains common [12, 18, 19]. Previous studies have reported insufficient public awareness regarding stroke symptoms and appropriate EMS activation, particularly among high-risk populations [8, 9]. Improving stroke-related health literacy has therefore become an important public health priority for enhancing access to timely stroke care.
Although several studies have investigated stroke knowledge, symptom recognition, or EMS utilization separately, comprehensive evidence regarding multidimensional stroke-related health literacy among patients with acute stroke remains limited [8-10]. Previous studies have primarily focused on a single aspect of health literacy and were often conducted in single-center settings, limiting the understanding of the broader factors influencing emergency healthcare-seeking behavior. In particular, little is known about patients' knowledge of stroke symptoms, perceived stroke severity, awareness of emergency medical services, attitudes toward EMS utilization, and healthcare access factors within a unified health literacy framework.
Given Thailand’s universal healthcare system and nationwide EMS network, identifying gaps in stroke-related health literacy may help optimize public health education and improve timely access to emergency stroke care. To our knowledge, no multicenter study has comprehensively evaluated these multidimensional health literacy domains among patients with acute stroke in Thailand. Addressing this knowledge gap may provide valuable evidence for developing targeted interventions to improve stroke recognition, promote appropriate EMS utilization, reduce prehospital delays, and ultimately improve stroke outcomes.
Therefore, this study primarily aimed to assess stroke-related health literacy and utilization of emergency medical services among patients with acute stroke in Thailand. In addition, factors associated with timely hospital arrival (≤4.5 hours) were examined to provide an analytical assessment of prehospital care.
2. MATERIALS AND METHODS
2.1. Study Design and Setting
A multicenter cross-sectional study was conducted among patients with acute stroke receiving care at four tertiary care hospitals in Thailand from January to May 2026. Data collection was initiated at each participating hospital only after the corresponding site-specific ethics approval had been obtained. Tertiary hospitals were selected because they function as referral centers for acute stroke care and provide the clinical and neuroimaging capacity required for definitive stroke diagnosis and management, while also providing sufficient patient volume for multicenter recruitment. The multicenter design permitted hospital-level clustering to be considered in the multivariable analysis.
This study was reported in accordance with the Strengthening the Reporting of Observational Studies in Epidemiology (STROBE) guidelines for cross-sectional studies [20].
2.2. Participants and Eligibility Criteria
The study population comprised adult patients aged 18 years or older who were diagnosed with acute stroke by attending physicians based on clinical presentation and neuroimaging findings according to national stroke guidelines. Participants were eligible if they were admitted to one of the participating tertiary hospitals during the study period, were able to provide information by themselves or through a legal representative/caregiver, and provided written informed consent.
Patients were excluded if they had severe cognitive impairment or communication difficulties that precluded completion of the questionnaire, were clinically unstable at the time of data collection, had incomplete medical records, or declined to participate in the study.
Both ischemic and hemorrhagic stroke were eligible for inclusion. Stroke subtype, body weight, and body mass index (BMI) were not included as variables in the final analytic dataset available for this study; therefore, subtype-specific and anthropometric descriptive statistics could not be reported.
2.3. Sampling Method
A multistage sampling approach was used. Health Region 9 was selected from the four health regions in northeastern Thailand using simple random sampling, and the four tertiary hospitals in the selected region, namely Maharaj Nakhon Ratchasima Hospital, Chaiyaphum Hospital, Buriram Hospital, and Surin Hospital, served as the study sites. The planned sample was allocated to the four hospitals using proportional-to-size sampling based on the number of stroke patients at each hospital. Within each hospital, eligible participants were recruited purposively according to the predefined eligibility criteria.
2.4. Sample Size
The required sample size for multivariable logistic regression was determined using the method of Hsieh et al. [21]. After accounting for correlations among independent variables, assuming a squared multiple correlation coefficient (R-squared) of 0.50, corresponding to a variance inflation factor (VIF) of 2.00, the required sample size was 1,252 participants. An allowance for potential attrition or incomplete data was incorporated, resulting in a planned sample size of 1,296 participants. Using proportional-to-size allocation based on the number of patients with stroke at each participating hospital, the planned sample was distributed as follows: 534 participants from Maharaj Nakhon Ratchasima Hospital, 182 from Chaiyaphum Hospital, 326 from Buriram Hospital, and 254 from Surin Hospital (planned total, n = 1,296).
2.5. Study Instrument
Data were collected using a structured questionnaire developed based on the health literacy framework proposed by Nutbeam and Sørensen et al. [4, 5], as well as relevant literature on stroke recognition and emergency medical services (EMS) utilization [2, 6].
The questionnaire was developed and administered in Thai; therefore, translation or back-translation was not required for study administration.
Representative questionnaire items were included to clarify the content of the instrument. Examples of stroke-knowledge items assessed whether patients should seek medical care as soon as possible when stroke symptoms occur and whether the national emergency medical service number (1669) should be called when stroke symptoms develop. Perceived-severity items included recognition of sudden speech difficulty, facial drooping, and unilateral weakness as possible manifestations of stroke. EMS-related items assessed expectations regarding response speed and safety, concerns about infection risk, difficulty in requesting emergency services, and perceptions that waiting could worsen the patient's condition.
(1) Stroke knowledge (10 items): assessed recognition of stroke symptoms and appropriate initial responses. Each correct answer was scored as 1 and each incorrect or "do not know" response as 0, yielding a total score of 0-10.
(2) Perceived stroke severity (5 items): assessed participants’ perceptions regarding the seriousness of stroke and the urgency of seeking medical care using a three-point rating scale.
(3) EMS awareness (3 items): assessed knowledge of the national EMS access number (1669), awareness of EMS availability, and previous EMS utilization.
(4) Attitudes and expectations toward EMS utilization (5 items): assessed participants’ expectations and attitudes regarding EMS use using a three-point rating scale.
(5) Healthcare access factors (6 items): assessed access to communication devices, transportation, caregiver support, prior stroke-related information, community EMS availability, and distance from residence to the hospital.
The questionnaire domains were analyzed and reported separately rather than combined into a single composite health-literacy score. Higher scores within the scored domains indicated greater stroke knowledge, higher perceived stroke severity, or more favorable attitudes and expectations toward EMS utilization, as applicable. EMS awareness and healthcare access factors were summarized as individual categorical indicators.
2.6. Instrument Validity and Reliability
Content validity was assessed by a panel of six experts in emergency medicine, stroke care, nursing, and public health. The questionnaire demonstrated excellent content validity, with an overall Content Validity Index (CVI) of 0.96 and Item-Objective Congruence (IOC) values ranging from 0.83 to 1.00, consistent with recommendations by Polit and Beck [22].
The revised questionnaire was pilot-tested with 30 participants who were similar in characteristics to the study population. Internal consistency reliability was evaluated using Cronbach's alpha coefficient for rating-scale domains and the Kuder-Richardson Formula 20 (KR-20) for dichotomous knowledge items [22, 23]. The questionnaire demonstrated satisfactory reliability, with a Cronbach's alpha coefficient of 0.91 and a KR-20 coefficient of 0.82.
2.7. Data Collection
Data were collected through standardized face-to-face interviews using a structured questionnaire and supplemented with information extracted from medical records. Trained research assistants conducted the interviews following standardized data collection procedures across all participating hospitals. To minimize information bias, medical records were reviewed to verify clinical information.
2.8. Outcome Measurement
Stroke-related health literacy was evaluated using multiple domains, including stroke knowledge, perceived stroke severity, attitudes and expectations toward emergency medical services (EMS) utilization, EMS awareness, and healthcare access factors, based on the conceptual framework of health literacy proposed by Nutbeam and Sørensen et al. [4, 5].
Stroke knowledge was assessed using ten dichotomous items (correct = 1, incorrect or "do not know" = 0), yielding a total score ranging from 0 to 10. Knowledge levels were classified as low (0-3 points), moderate (4-7 points), and high (8-10 points).
Perceived stroke severity and attitudes and expectations toward EMS utilization were assessed using three-point rating-scale items. Domain scores were converted to percentage scores and categorized according to the prespecified scoring criteria used in the study: low (<60%), moderate (60-79%), and high (≥80%). These categories were used for describe the separate domains and were not combined into an overall health-literacy score.
EMS awareness was assessed using participants' knowledge of the national EMS access number (1669), prior EMS utilization, and awareness of EMS availability. Healthcare access factors included availability of communication devices, transportation resources, prior receipt of stroke-related information, caregiver support, and distance from residence to the hospital.
2.9. Statistical Analysis
Statistical analyses were performed using Stata Statistical Software, Release 14 (StataCorp LLC, College Station, TX, USA). Descriptive statistics summarized sociodemographic, clinical, stroke-related health literacy, EMS-related, and healthcare access characteristics. Categorical variables were reported as frequencies and percentages, and continuous variables as means and standard deviations or medians and ranges, as appropriate. Timely hospital arrival (≤4.5 hours) was treated as a binary outcome. Univariable logistic regression was used to examine crude associations. Multivariable analysis was performed using a generalized linear mixed model (GLMM), with hospital included as a random effect to account for clustering within the four participating hospitals. Results are presented as adjusted odds ratios (aORs), 95% confidence intervals (CIs), and p-values; p<0.05 was considered statistically significant.
No missing data were identified for variables included in the final analysis.
2.10. Ethical Considerations
The study protocol was approved by the Khon Kaen University Ethics Committee for Human Research (Reference No. HE682181) on November 14, 2025. Site-specific ethics approvals were subsequently obtained from Surin Hospital on January 30, 2026; Chaiyaphum Hospital on March 31, 2026; Maharaj Nakhon Ratchasima Hospital on April 29, 2026; and Buriram Hospital on April 30, 2026. Data collection at each participating hospital commenced only after the respective site-specific ethics approval had been obtained. Written informed consent was obtained from all participants or their legal representatives before participation. All study procedures were conducted in accordance with the ethical principles of the Declaration of Helsinki.
3. RESULTS
The participant recruitment and inclusion process is presented in Fig. (1). During actual recruitment, a total of 1,350 patients were assessed for eligibility. Fifty-eight were excluded (20 declined participation, 18 had incomplete questionnaires, and 20 had incomplete medical records), resulting in 1,292 participants being included in the final analysis. Final site-specific participant counts were not available for reporting; therefore, hospital-specific counts for the final analytic sample are not presented.
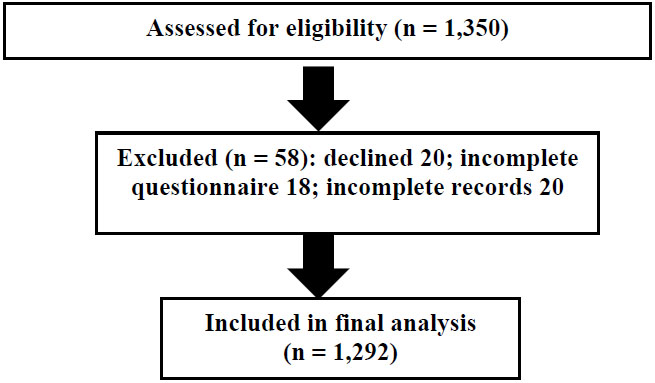
Table 1 presents the sociodemographic and clinical characteristics of the study participants. More than half were male (52.6%) and younger than 60 years (60.2%). The majority were married (65.0%) and had completed secondary education (49.5%). Agriculture/labor was the predominant occupation (43.3%). A history of previous stroke was reported by 20.1% of participants, and 39.5% had underlying diseases.
| Characteristics | n | % |
|---|---|---|
| Sex | ||
| Male | 680 | 52.6 |
| Female | 612 | 47.4 |
| Age (years) | ||
| 18 years | 24 | 1.9 |
| 19-30 years | 56 | 4.3 |
| 31-45 years | 198 | 15.3 |
| 46-60 years | 504 | 39.0 |
| ≥60 years | 510 | 39.5 |
| Marital status | ||
| Single | 312 | 24.1 |
| Married | 840 | 65.0 |
| Widowed/Divorced | 140 | 10.8 |
| Education | ||
| Primary school or lower | 330 | 25.5 |
| Secondary school | 640 | 49.5 |
| Higher education | 322 | 24.9 |
| Occupation | ||
| Agriculture/Labor | 560 | 43.3 |
| Self-employed | 300 | 23.2 |
| Government officer | 262 | 20.3 |
| Others | 170 | 13.2 |
| Previous stroke | 260 | 20.1 |
| Underlying diseases | 510 | 39.5 |
| Stroke severity (NIHSS) | ||
| Mild (1-4 points) | 230 | 17.8 |
| Moderate (5-15 points) | 580 | 44.9 |
| Severe (≥16 points) | 482 | 37.3 |
The mean age was 55.5 ± 13.5 years, with a median age of 56 years (range 18-80 years). Participants were distributed across the following age groups: 18 years, 24 (1.9%); 19-30 years, 56 (4.3%); 31-45 years, 198 (15.3%); 46-60 years, 504 (39.0%); and ≥60 years, 510 (39.5%).
NIHSS severity was mild in 230 participants (17.8%), moderate in 580 (44.9%), and severe (≥16 points) in 482 (37.3%).
Both ischemic and hemorrhagic stroke patients were included; however, stroke subtype, body weight, and BMI were not included as variables in the final analytic dataset available for this study. Accordingly, subtype-specific counts and anthropometric descriptive statistics are not reported.
Table 2 shows that most participants had a moderate level of stroke knowledge (46.4%), followed by low (31.9%) and high (21.7%). However, 49.5% were aware of the national EMS access number (1669), indicating insufficient awareness of emergency medical services among a substantial proportion of participants.
| Knowledge Level | n | % |
|---|---|---|
| Low (0-3 points) | 412 | 31.9 |
| Moderate (4-7 points) | 600 | 46.4 |
| High (8-10 points) | 280 | 21.7 |
As shown in Table 3, perceived stroke severity was predominantly moderate (38.7%). Approximately one-third of participants (31.0%) reported low perceived severity, while 30.3% reported high perceived severity.
| Perceived Severity Level | n | % |
|---|---|---|
| Low (<60%) | 400 | 31.0 |
| Moderate (60-79%) | 500 | 38.7 |
| High (≥80%) | 392 | 30.3 |
Table 4 shows that the majority of participants had moderate expectations and attitudes toward EMS utilization (43.3%), followed by low (33.3%) and high (23.4%).
| Level | n | % |
|---|---|---|
| Low | 430 | 33.3 |
| Moderate | 560 | 43.3 |
| High | 302 | 23.4 |
Table 5 presents enabling and healthcare access factors among the participants. Most participants reported residing more than 35 kilometers from the hospital (69.0%), while 59.6% reported that EMS units were available in their communities. Awareness of the national EMS access number (1669) was reported by 49.5% of participants, and 48.4% had previous experience using EMS. More than half reported having access to communication devices (68.2%), transportation (63.5%), prior stroke-related information (56.5%), and caregiver support (60.5%).
| Variables | n | % |
|---|---|---|
| Distance ≥35 km | 892 | 69.0 |
| EMS unit in community | 770 | 59.6 |
| Awareness of EMS number (1669) | 640 | 49.5 |
| Previous EMS utilization | 625 | 48.4 |
| Communication device available | 880 | 68.2 |
| Transportation available | 820 | 63.5 |
| Received stroke-related information | 730 | 56.5 |
| Caregiver support available | 782 | 60.5 |
Table 6 summarizes the major domains of stroke-related health literacy. Moderate levels predominated across stroke knowledge (46.4%), perceived stroke severity (38.7%), and expectations and attitudes toward EMS utilization (43.3%). Awareness of the national EMS access number (1669) was reported by 49.5% of participants, 48.4% had prior EMS utilization experience, and 56.5% had previously received stroke-related information.
| Domain | Predominant Level | % |
|---|---|---|
| Stroke knowledge | Moderate | 46.4 |
| Perceived stroke severity | Moderate | 38.7 |
| Expectations and attitudes toward EMS | Moderate | 43.3 |
| Awareness of EMS number (1669) | Aware | 49.5 |
| Previous EMS utilization | Yes | 48.4 |
| Received stroke-related information | Yes | 56.5 |
3.1. Timely Hospital Arrival and Multivariable Analysis
Of the 1,292 participants, 650 (50.3%) arrived at the hospital within 4.5 hours of symptom onset, whereas 642 (49.7%) arrived more than 4.5 hours after symptom onset.
In the multivariable GLMM, sudden symptom onset was associated with higher odds of timely arrival (aOR 2.50, 95% CI 1.85-3.35, p<0.001). Compared with mild stroke severity, moderate NIHSS severity (aOR 2.00, 95% CI 1.40-2.85, p<0.001) and severe NIHSS severity (aOR 4.50, 95% CI 2.80-7.20, p<0.001) were independently associated with timely arrival. Awareness of the national EMS number 1669 (aOR 1.70, 95% CI 1.30-2.20, p<0.001), caregiver assistance for hospital transportation (aOR 3.75, 95% CI 2.79-5.05, p<0.001), and distance ≥35 km (aOR 4.10, 95% CI 3.00-5.60, p<0.001) also remained significantly associated with timely arrival. The multivariable results are presented in Table 7.
| Factor | Reference Category | Adjusted OR | 95% CI | p-value |
|---|---|---|---|---|
| Sudden symptom onset | Gradual or intermittent | 2.50 | 1.85-3.35 | <0.001 |
| NIHSS: Moderate | Mild | 2.00 | 1.40-2.85 | <0.001 |
| NIHSS: Severe | Mild | 4.50 | 2.80-7.20 | <0.001 |
| Awareness of EMS number 1669 | Not aware | 1.70 | 1.30-2.20 | <0.001 |
| Caregiver assistance | No assistance | 3.75 | 2.79-5.05 | <0.001 |
| Distance ≥35 km | <35 km | 4.10 | 3.00-5.60 | <0.001 |
4. DISCUSSION
4.1. Principal Findings
This multicenter cross-sectional study assessed stroke-related health literacy and EMS utilization and examined factors associated with timely hospital arrival among patients with acute stroke in Thailand. Health literacy was predominantly moderate across stroke knowledge, perceived stroke severity, and attitudes toward EMS utilization, while awareness of the national EMS number remained limited. Approximately half of participants arrived within 4.5 hours. In the multivariable analysis, sudden symptom onset, greater NIHSS severity, awareness of 1669, caregiver assistance, and distance from the hospital were independently associated with timely arrival. These findings indicate that timely stroke care is shaped by both recognition-related and access-related factors.
Notably, the finding that residence ≥35 km from the hospital was associated with higher odds of timely arrival appears counterintuitive and should be interpreted with caution. One possible explanation is transfer bias related to the referral role of the participating tertiary hospitals. Patients residing farther away may have been more likely to enter organized EMS or interfacility referral pathways, potentially facilitating coordinated transportation and transfer to tertiary stroke centers. In contrast, the present study did not capture detailed information on referral origin, interfacility transfer, or prehospital transport pathways; therefore, this mechanism could not be directly evaluated. Accordingly, the observed association should not be interpreted as indicating that greater geographic distance itself promotes timely hospital arrival, but may partly reflect differences in referral and transfer patterns among patients reaching the participating tertiary hospitals.
4.2. Comparison with Previous Studies
The findings of the present study are consistent with previous studies showing that inadequate health literacy is associated with poor recognition of stroke symptoms, inappropriate healthcare-seeking behavior, and delayed utilization of emergency medical services (EMS) [4-6, 8-14, 24]. Studies conducted in Thailand and other Asian countries have similarly reported limited awareness of stroke symptoms and emergency service activation, contributing to delayed hospital arrival and reduced access to time-sensitive stroke treatment [8-14, 19, 24]. The finding that fewer than half of the participants correctly identified the national EMS number (1669) further highlights persistent gaps in emergency preparedness. Collectively, these findings underscore the potential importance of stroke-related health literacy for timely access to acute stroke care; however, the cross-sectional design does not establish that improving health literacy will translate into better clinical outcomes.
4.3. Public Health Implications
The findings have important implications for public health policy in Thailand. Strengthening community-based stroke education, public awareness of the national EMS number (1669), and caregiver preparedness may improve activation of emergency care. The findings may also inform health-promotion strategies in other low- and middle-income settings facing comparable challenges in stroke recognition, prehospital care, and EMS access; however, differences in EMS organization and healthcare systems should be considered when extrapolating these findings beyond Thailand [2, 13].
4.4. EMS Education Implications
Education regarding EMS utilization should be incorporated into national stroke prevention programs and community health promotion activities. Given that fewer than half of participants correctly identified the national EMS number (1669), targeted educational interventions should emphasize awareness of EMS access and the importance of early activation of emergency services. Healthcare professionals, emergency medical personnel, and primary healthcare workers should collaborate to improve public understanding of EMS utilization through community-based education and health promotion activities. Public campaigns emphasizing the FAST message and the importance of calling 1669 immediately after symptom onset may support appropriate EMS utilization and earlier care-seeking [2, 8, 9, 14].
4.5. Strengths
This study included a large sample of 1,292 patients with acute stroke recruited from four tertiary care hospitals. The multicenter design and use of a hospital-level random effect in the GLMM strengthened the analysis by accounting for clustering across study sites. The study also examined multiple health-literacy, clinical, EMS, and access-related domains relevant to timely stroke care.
LIMITATIONS
Several limitations should be considered. First, the cross-sectional design precludes causal inference; therefore, the observed associations should not be interpreted as evidence that the identified factors caused earlier hospital arrival or improved clinical outcomes. Second, questionnaire data were self-reported and may be affected by recall and social desirability bias. Third, stroke-related health literacy was assessed after hospital admission; responses may therefore have been influenced by information received during hospitalization, potentially leading to an overestimation of pre-event health literacy. Fourth, recruitment was limited to tertiary hospitals, creating potential selection bias and limiting generalizability to patients managed in primary or secondary healthcare settings and to other healthcare systems. Patients who died before hospital assessment or were otherwise unable to enter the recruitment process may have been underrepresented, introducing potential survivor bias. Finally, differences among participating hospitals may have introduced center effects; hospital-level clustering was therefore addressed by including hospital as a random effect in the GLMM. Future longitudinal and intervention studies should evaluate whether improvements in stroke-related health literacy and EMS awareness are associated with earlier EMS activation, shorter prehospital delays, and better clinical outcomes. In addition, detailed information on referral origin, interfacility transfer, and prehospital transport pathways was unavailable; therefore, transfer bias may partly explain the counterintuitive association between residence ≥35 km from the hospital and higher odds of timely arrival. In addition, body weight, BMI, and stroke subtype were not included as variables in the final analytic dataset available for this study; consequently, their distributions and potential associations could not be evaluated in this analysis.
CONCLUSION
This multicenter cross-sectional study found that stroke-related health literacy among patients with acute stroke in Thailand was generally moderate, with persistent gaps in EMS awareness. Approximately half of participants arrived at the hospital within 4.5 hours. Sudden symptom onset, greater stroke severity, awareness of the national EMS number 1669, caregiver assistance, and distance from the hospital were independently associated with timely arrival. Public health strategies should therefore combine stroke-symptom education with EMS awareness and practical support for emergency access. These findings may also be informative for settings facing similar prehospital stroke-care challenges, while acknowledging differences between healthcare systems.
AUTHORS' CONTRIBUTIONS
Author-identifying contribution details have been blinded for peer review and will be restored after acceptance.
LIST OF ABBREVIATIONS
| CVI | = Content Validity Index |
| DALYs | = Disability-Adjusted Life Years |
| EMS | = Emergency Medical Services |
| FAST | = Face, Arm, Speech, Time |
| GBD | = Global Burden of Disease |
| IOC | = Item-Objective Congruence |
| KR-20 | = Kuder-Richardson Formula 20 |
ETHICS APPROVAL AND CONSENT TO PARTICIPATE
The study protocol was approved by the Khon Kaen University Ethics Committee for Human Research (Reference No. HE682181) on November 14, 2025. Site-specific ethics approvals were subsequently obtained from Surin Hospital on January 30, 2026; Chaiyaphum Hospital on March 31, 2026; Maharaj Nakhon Ratchasima Hospital on April 29, 2026; and Buriram Hospital on April 30, 2026. Data collection at each participating hospital commenced only after the respective site-specific ethics approval had been obtained.
HUMAN AND ANIMAL RIGHTS
No animals were used in this research. All procedures performed in studies involving human participants were in accordance with the ethical standards of institutional and/or research committees and with the 1975 Declaration of Helsinki, as revised in 2013.
CONSENT FOR PUBLICATION
Written informed consent was obtained from all participants or their legal representatives prior to participation.
AVAILABILITY OF DATA AND MATERIAL
All the data and supporting material is available within the article.
ACKNOWLEDGEMENTS
The authors would like to express their sincere gratitude to all participants and the healthcare professionals at the participating hospitals for their valuable cooperation. The authors also thank the experts who contributed to the development and validation of the research instrument.

