All published articles of this journal are available on ScienceDirect.

Determinants of Emergency Management Behavior for Non-Communicable Disease Emergencies Among Patients with Uncontrolled Type 2 Diabetes in Rural Thailand

Abstract
Introduction/Objective
Effective emergency management is essential for preventing serious complications among people with poorly controlled Type 2 Diabetes Mellitus (T2DM) in rural primary health care settings. This study examined how health beliefs, social-contextual factors, and self-efficacy are associated with emergency management behavior in rural Thailand.
Methods
This cross-sectional study included 1,074 adults with poorly controlled T2DM attending rural primary health care services. Participants completed a theory-informed questionnaire. Structural equation modeling was used to examine direct and indirect relationships among health beliefs, community participation, social support, self-efficacy, and emergency management behavior.
Results
The model explained 77.6% of the variance in emergency management behavior. Community participation was the strongest predictor of both self-efficacy and emergency management behavior. Self-efficacy was independently associated with better emergency management behavior and mediated the effects of social-contextual factors. Among Health Belief Model constructs, only perceived severity was directly associated with emergency management behavior.
Discussion
Social engagement and efficacy beliefs, rather than most Health Belief Model perceptions, accounted for emergency management behavior in this population, with self-efficacy linking social-contextual resources to behavior.
Conclusion
Community participation, self-efficacy, and perceived severity were the factors most strongly associated with emergency management behavior in this population. Strengthening community-based diabetes care and enhancing self-efficacy may support emergency preparedness in rural primary health care settings and inform strategies for similar resource-constrained communities.
1. INTRODUCTION
Primary health care systems across the Asia-Pacific region face growing challenges in delivering effective chronic disease care, particularly in resource-constrained settings [1]. In Thailand, poorly controlled Type 2 Diabetes Mellitus (T2DM) contributes substantially to this burden because it increases the risk of acute complications, including hypoglycemic crises, hypertensive emergencies, and acute coronary syndromes. These events frequently occur outside healthcare facilities and require timely recognition and response by patients and family members. In rural settings, where access to emergency services and specialist care may be limited, effective household emergency management is essential for reducing disability, preventing complications, and improving survival outcomes [2, 3]. At the provincial level, this challenge is evident in Sisaket Province, northeastern Thailand, where rates of glycemic and blood pressure control among registered patients with T2DM remain below national targets. Although considerable attention has been devoted to diabetes self-management, including the role of self-efficacy, psychological stress, and family support in shaping routine self-care behaviors [4, 5], relatively little is known about the psychosocial factors that influence emergency management behavior in rural communities, particularly among individuals living with poorly controlled T2DM [6]. More importantly, existing evidence has largely focused on identifying factors associated with health-related behaviors, while the mechanisms through which psychosocial influences shape emergency management behavior remain insufficiently understood. It is unclear whether such behavior is driven primarily by cognitive beliefs regarding disease threats and benefits of action, by social and community influences, or by individuals’ confidence in their ability to respond effectively during emergencies. Understanding these mechanisms is critical for designing interventions that target the most influential behavioral pathways rather than merely addressing isolated risk factors. The present study therefore departs from previous research on diabetes self-management and emergency preparedness in two respects: it takes emergency management behavior, rather than routine self-care, as the outcome of interest, and it specifies self-efficacy as an explicit mediating mechanism linking social-contextual resources to that behavior, rather than treating psychosocial variables solely as independent correlates.
The Health Belief Model (HBM) and Social Cognitive Theory (SCT) provide complementary theoretical frameworks for understanding these issues. HBM proposes that health-related actions are influenced by perceived susceptibility, perceived severity, perceived benefits, and perceived barriers [7], whereas SCT emphasizes self-efficacy and the influence of social and environmental contexts on behavior [8]. Together, these theories offer a comprehensive framework for understanding how individual beliefs, social support, community participation, and confidence in one’s abilities interact to influence behavioral responses during acute non-communicable disease (NCD)-related emergencies. Accordingly, the present study was designed to address the following theoretical question: through what mechanisms do HBM and SCT constructs influence emergency management behavior among patients with T2DM in rural communities? Guided by these theoretical perspectives, the study conceptualized emergency management behavior as a function of cognitive perceptions, knowledge, social-environmental influences, and self-efficacy. In addition, the study characterized the prevalence and context of acute NCD-related emergency events to provide a practical context for interpreting behavioral responses in the target population. The primary aim of this study was to examine the psychosocial mechanisms underlying emergency management behavior among patients with uncontrolled type 2 diabetes using a theory-driven model derived from the Health Belief Model and Social Cognitive Theory. Secondary objectives were to characterize emergency management behavior and describe the prevalence and context of acute emergency events.
2. METHODOLOGY
2.1. Study Design, Conceptual Framework, and Participants
A cross-sectional analytical study was conducted from March to May 2026 among patients with T2DM registered in Sisaket Province, northeastern Thailand. This study was approved by the Human Research Ethics Committee of Sisaket Province (No. SPPH 2026-034, dated 18 February 2026). All procedures were conducted in accordance with the ethical standards of the Declaration of Helsinki, and informed consent was obtained from all participants prior to data collection. The study was guided by a conceptual framework derived from the HBM [7] and SCT [9]. Consistent with these theories, emergency management behavior was conceptualized as being influenced by cognitive factors, including knowledge, perceived susceptibility, perceived severity, perceived benefits, and perceived barriers, as well as social-environmental factors, including social support and community participation. Based on SCT, self-efficacy was hypothesized to function as a key mediating mechanism through which psychosocial factors influence emergency management behavior. The hypothesized model was subsequently evaluated using Structural Equation Modeling (SEM).
The target population comprised patients with T2DM and documented poor glycemic or blood pressure control registered across all 22 districts of Sisaket Province. Information on glycemic and blood pressure control status was obtained from routine clinical records maintained by healthcare facilities. Poor glycemic control was defined as HbA1c above the recommended treatment target, whereas poor blood pressure control was defined as blood pressure above the recommended target according to national clinical practice guidelines. Participants were enrolled through a stratified multistage random sampling procedure [10] operating at three levels: district, primary care unit, and individual patient. All 22 districts of Sisaket Province were included as strata, with questionnaires allocated in proportion to the registered population of patients with uncontrolled T2DM in each district. Within each district, primary care units were randomly selected from the provincial health facility registry. Eligible patients were then selected from the T2DM registry of each unit by simple random sampling until the district quota was reached. The minimum sample size was estimated a priori using G*Power 3.1 (multiple regression, fixed model) with a small anticipated effect size (f2 = 0.02), α = 0.05, power = 0.80, and 14 predictors, and was increased by 15% to allow for non-response, yielding a target of 1,070 participants. Sample adequacy for SEM was evaluated against model complexity [11], using the ratio of cases to freely estimated parameters, for which a minimum of 5:1 has been recommended [12]. The structural model contained 144 freely estimated parameters; the final analytic sample of 1,074 therefore provided a ratio of 7.5:1.
2.2. Research Instrument
An 82-item interviewer-administered questionnaire was developed by the research team based on constructs derived from the HBM and SCT, together with relevant literature on diabetes emergency management. Questionnaire domains were mapped directly to the theoretical constructs specified in the study’s conceptual framework. The questionnaire comprised seven sections covering ten domains: sociodemographic characteristics (12 items), knowledge (10 dichotomous items), the four Health Belief Model perception subscales, perceived susceptibility, perceived severity, perceived benefits, and perceived barriers (5 items each, administered as a single section), social support (10 items), community participation (10 items), self-efficacy (10 items), and emergency management behavior (10 items). Content validity was evaluated by three experts in diabetes care, behavioral science, and public health, yielding item-objective congruence (IOC) values ranging from 0.67 to 1.00; all items therefore met the conventional retention criterion of IOC ≥ 0.50 and were carried forward without deletion. Internal consistency reliability was assessed through pilot testing, with all Likert-scale subscales demonstrating acceptable reliability (Cronbach’s α ≥ 0.70). Interviewers received standardized training prior to data collection to ensure consistency in questionnaire administration and data recording.
2.3. Statistical Analysis
Data were analyzed using R version 4.4.1 (R Foundation for Statistical Computing, Vienna, Austria) within the RStudio integrated development environment (version 2023.06.0+421). Descriptive statistics were used to summarize participant characteristics and study variables. Internal consistency reliability of latent constructs was evaluated using Cronbach’s alpha and McDonald’s omega coefficients. Structural equation modeling was conducted following recommended procedures described by Kline (2023), with model fit evaluated using established criteria. First, Confirmatory Factor Analysis (CFA) was performed using the lavaan package to evaluate the measurement model derived from the Health Belief Model (HBM) and Social Cognitive Theory (SCT). Model fit was assessed using the Comparative Fit Index (CFI), Tucker-Lewis Index (TLI), Root Mean Square Error of Approximation (RMSEA), and Standardized Root Mean Square Residual (SRMR), based on commonly recommended criteria (CFI and TLI ≥ 0.90; RMSEA and SRMR ≤ 0.08) [13]. Convergent validity was assessed using the Fornell-Larcker criterion: Average Variance Extracted (AVE) values ≥ 0.50 indicate adequate convergent validity [14]. After establishing an acceptable measurement model, a theory-driven structural model was specified a priori based on HBM and SCT. Knowledge was assessed descriptively and was not included in the SEM because it was not specified as a latent construct in the theoretical model. The model hypothesized that cognitive perceptions (perceived susceptibility, perceived severity, perceived benefits, and perceived barriers) and social-environmental factors (social support and community participation) would influence emergency management behavior directly and indirectly through self-efficacy. Structural relationships were estimated using robust maximum likelihood estimation. Indirect effects were evaluated using bias-corrected bootstrap procedures with 2,000 resamples [15]. Mediation effects were considered statistically significant when the 95% bootstrap confidence interval did not include zero. The explanatory power of the model was assessed using coefficients of determination (R2) for self-efficacy and emergency management behavior. Statistical significance was defined as p < .05. No missing data were observed for variables included in the analyses. Therefore, no imputation procedures were required. Duration of illness, a continuous variable, was additionally grouped into four categories (1-5, 6-10, 11-15, and >15 years) for descriptive presentation, reflecting intervals commonly used in prior diabetes research to distinguish early, intermediate, and long-standing disease duration; this categorization was used for descriptive purposes only and was not applied in the structural equation model. Although a multistage random sampling procedure was used for participant selection, the structural equation modeling analysis treated observations as independent; potential clustering effects arising from the multistage sampling design were not explicitly modeled and are acknowledged as a limitation of the analytical approach.
2.4. Reporting Standards
This manuscript was prepared and reported in accordance with the Strengthening the Reporting of Observational Studies in Epidemiology (STROBE) Statement for cross-sectional studies [16]. A completed STROBE checklist is included as Supplementary Material.
3. RESULTS
3.1. Participant Characteristics
A total of 1,104 records were initially available for analysis. Prior to model estimation, data screening was conducted to identify implausible values and data entry errors. Thirty records with age values outside the predefined eligibility range (<18 or >100 years) were excluded. The final analytic sample comprised 1,074 participants and was used for all subsequent analyses, including confirmatory factor analysis and structural equation modeling (Table 1). Missing data were minimal; duration of illness was available for 1,070 of 1,074 participants (99.6%), and no missing values were observed for any other sociodemographic, clinical, or study variable.
| Characteristic | n (%) or Mean ± SD |
|---|---|
| Sex | |
| Male | 343 (31.9) |
| Female | 731 (68.1) |
| Age (years) | 64.62 ± 11.84 |
| Age range (years) | 25-97 |
| Education level | |
| No formal education | 66 (6.2) |
| Primary education | 779 (72.5) |
| Lower secondary education | 135 (12.6) |
| Upper secondary/Vocational education | 83 (7.7) |
| Bachelor's degree or higher | 11 (1.0) |
| Occupation | |
| Farmer | 939 (87.4) |
| Merchant/Business owner | 45 (4.2) |
| Laborer | 46 (4.3) |
| Government officer/State enterprise employee | 8 (0.7) |
| Other | 36 (3.4) |
| Living arrangement | |
| Living alone | 67 (6.2) |
| Living with spouse | 323 (30.1) |
| Living with children or household members (>3 persons) | 506 (47.1) |
| Living with relatives (>5 persons) | 166 (15.5) |
| Other | 12 (1.1) |
| Duration of illness (years)* | 10.1 ± 5.4 |
| 1-5 years | 218 (20.4) |
| 6-10 years | 347 (32.4) |
| 11-15 years | 289 (27.0) |
| >15 years | 216 (20.2) |
| Primary caregiver status | |
| Independent self-care | 841 (78.3) |
| Partially dependent; cared for by children | 210 (19.6) |
| Dependent; government caregiver support | 8 (0.7) |
| Dependent; cared for by spouse | 15 (1.4) |
| Treatment modality | |
| Oral medication only | 963 (89.7) |
| Oral medication and insulin injection | 34 (3.2) |
| Lifestyle modification only | 69 (6.4) |
| Other treatment (e.g., dialysis) | 8 (0.7) |
3.2. Measurement Model Evaluation
Prior to testing the hypothesized structural relationships, the measurement model was evaluated using Confirmatory Factor Analysis (CFA). The model comprised eight latent constructs derived from the Health Belief Model (HBM) and Social Cognitive Theory (SCT), including perceived susceptibility, perceived severity, perceived benefits, perceived barriers, social support, community participation, self-efficacy, and emergency management behavior. The CFA demonstrated acceptable model fit to the observed data (χ2 = 7,468.91, df = 1,682, CFI = 0.932, TLI = 0.929, RMSEA = 0.056, SRMR = 0.031), indicating that the hypothesized latent structure adequately represented the observed indicators. All constructs exhibited excellent internal consistency reliability. Cronbach’s alpha coefficients ranged from 0.934 to 0.975, while McDonald’s omega coefficients ranged from 0.935 to 0.975. Convergent validity was also supported, with Average Variance Extracted (AVE) values ranging from 0.741 to 0.822, exceeding the recommended threshold of 0.50 for all latent constructs. Overall, these findings provided adequate psychometric support for the measurement model and justified proceeding to structural model evaluation (Table 2).
| Construct | Cronbach's α | McDonald's ω | AVE | √AVE | Factor loading range |
|---|---|---|---|---|---|
| Perceived Susceptibility (SUS) | 0.955 | 0.956 | 0.813 | 0.902 | 0.883-0.918 |
| Perceived Severity (SEV) | 0.958 | 0.958 | 0.822 | 0.907 | 0.880-0.925 |
| Perceived Benefits (BEN) | 0.956 | 0.957 | 0.816 | 0.903 | 0.863-0.932 |
| Perceived Barriers (BAR) | 0.934 | 0.935 | 0.741 | 0.861 | 0.824-0.882 |
| Social Support (SS) | 0.968 | 0.968 | 0.754 | 0.868 | 0.817-0.901 |
| Community Participation (PAR) | 0.968 | 0.968 | 0.751 | 0.867 | 0.777-0.911 |
| Self-Efficacy (SE) | 0.975 | 0.975 | 0.797 | 0.893 | 0.846-0.911 |
| Emergency Management Behavior (BEH) | 0.975 | 0.975 | 0.795 | 0.892 | 0.814-0.915 |
Note: AVE = Average Variance Extracted. Recommended thresholds: Cronbach's α ≥ 0.70, McDonald's ω ≥ 0.70, AVE ≥ 0.50, and standardized factor loading ≥ 0.50. CFI = Comparative Fit Index; TLI = Tucker-Lewis Index; RMSEA = Root Mean Square Error of Approximation; SRMR = Standardized Root Mean Square Residual.
Discriminant validity was generally supported across constructs. However, social support and community participation exhibited a high latent correlation (r = 0.886), and the corresponding heterotrait-monotrait ratio (HTMT) value (0.890) slightly exceeded the more conservative threshold of 0.85, although it remained below the 0.90 criterion commonly applied to conceptually similar constructs [17]. These findings suggest partial conceptual overlap between the two social-contextual constructs. Both constructs were nevertheless retained, for two reasons. First, they represent theoretically distinct domains, the former referring to perceived interpersonal
assistance and the latter to active engagement in collective health activities. Second, they displayed markedly different associations within the structural model: community participation was associated with both self-efficacy (β = 0.646) and emergency management behavior (β = 0.441), whereas social support was associated with self-efficacy (β = 0.246) but not directly with behavior (β = 0.030, p = .571). This divergent pattern indicates that the two constructs are not interchangeable within the hypothesized model.
3.3. Structural Model Results
Following confirmation of an acceptable measurement model, the hypothesized structural model derived from the HBM and SCT was evaluated. As presented in Table 3 (Panel A), the structural model demonstrated acceptable fit to the observed data (χ2 = 7,486.64, df = 1,686, χ2/df = 4.44, CFI = 0.932, TLI = 0.929, RMSEA = 0.056, SRMR = 0.032), indicating that the proposed theoretical framework adequately represented the relationships among cognitive perceptions, social-contextual influences, self-efficacy, and emergency management behavior. The model explained 75.9% of the variance in self-efficacy (R2 = 0.759) and 77.6% of the variance in emergency management behavior (R2 = 0.776), indicating substantial explanatory power. With respect to the predictors of self-efficacy, Table 3 (Panel B) shows that both social support and community participation demonstrated significant positive effects. Community participation showed the strongest association with self-efficacy (β = 0.646, p < .001), followed by social support (β = 0.246, p < .001). Regarding predictors of emergency management behavior, Panel B further reveals that three variables demonstrated significant direct effects. Community participation emerged as the strongest predictor (β = 0.441, p < .001), followed by self-efficacy (β = 0.281, p < .001) and perceived severity (β = 0.203, p < .001). In contrast, perceived susceptibility (β = 0.001, p = .958), perceived benefits (β = −0.001, p = .950), perceived barriers (β = −0.017, p = .490), and social support (β = 0.030, p = .571) were not significantly associated with behavior after controlling for other variables in the model. The final structural model used for hypothesis testing is illustrated in Fig. (1). Standardized coefficients are shown for statistically significant pathways only (p < .001).
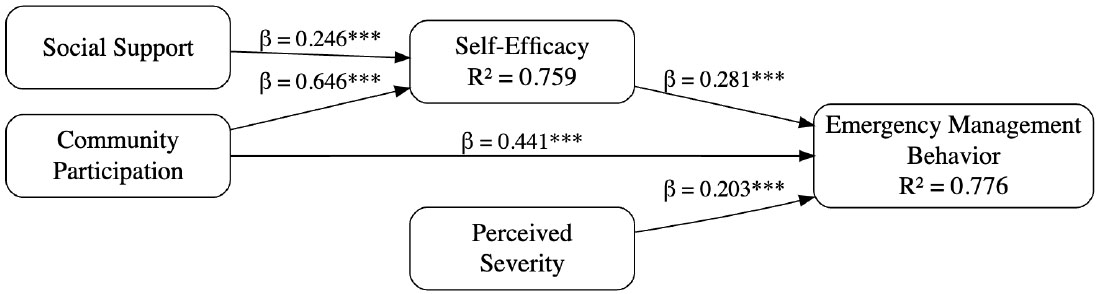
Final structural equation model of emergency management behavior. Standardized path coefficients are shown for statistically significant pathways only (p < .001); non-significant pathways specified in the model are omitted from the figure for clarity. Estimates for all specified pathways, including non-significant ones, are reported in Table 3.
| Fit Index | Value |
|---|---|
| χ2 | 7,486.64 |
| df | 1,686 |
| χ2/df | 4.44 |
| CFI | 0.932 |
| TLI | 0.929 |
| RMSEA | 0.056 |
| SRMR | 0.032 |
| Structural Path | *β | SE | z | 95% CI | p |
|---|---|---|---|---|---|
| Predictors of Self-Efficacy | |||||
| Social Support → Self-Efficacy | 0.246 | 0.056 | 4.417 | [0.136, 0.356] | < .001 |
| Community Participation → Self-Efficacy | 0.646 | 0.055 | 11.787 | [0.538, 0.754] | < .001 |
| Predictors of Emergency Management Behavior | |||||
| Perceived Susceptibility → Behavior | 0.001 | 0.028 | 0.052 | [−0.054, 0.056] | .958 |
| Perceived Severity → Behavior | 0.203 | 0.036 | 5.580 | [0.132, 0.274] | < .001 |
| Perceived Benefits → Behavior | −0.001 | 0.021 | −0.062 | [−0.042, 0.040] | .950 |
| Perceived Barriers → Behavior | −0.017 | 0.025 | −0.690 | [−0.066, 0.032] | .490 |
| Social Support → Behavior | 0.030 | 0.052 | 0.566 | [−0.072, 0.132] | .571 |
| Community Participation → Behavior | 0.441 | 0.060 | 7.396 | [0.323, 0.559] | < .001 |
| Self-Efficacy → Behavior | 0.281 | 0.045 | 6.296 | [0.193, 0.369] | < .001 |
3.4. Mediation Analysis
Bootstrap mediation analysis demonstrated significant indirect effects of both social support and community participation on emergency management behavior through self-efficacy (Table 4). Social support exhibited a significant indirect effect through self-efficacy (β = 0.069, 95% CI [0.037, 0.115], p < .001), whereas its direct effect on behavior was not statistically significant (β = 0.030, p = .571). This pattern corresponds to indirect-only mediation as defined by Zhao et al. [18], in which a significant indirect effect occurs alongside a non-significant direct effect. The total effect of social support on behavior was not statistically significant (β = 0.099, 95% CI [−0.007, 0.217], p = .079); under contemporary mediation frameworks, a significant total effect is not a precondition for establishing an indirect effect, and the more precisely estimated indirect pathway indicates that social support was associated with emergency management behavior primarily through self-efficacy.
| Indirect Pathway | Standardized β | 95% CI | p-value |
|---|---|---|---|
| Social Support → Self-Efficacy → Behavior | 0.069 | [0.037, 0.115] | < .001 |
| Community Participation → Self-Efficacy → Behavior | 0.182 | [0.133, 0.281] | < .001 |
| Total Pathway | Standardized β | 95% CI | p-value |
|---|---|---|---|
| Social Support → Behavior | 0.099 | [-0.007, 0.217] | .079 |
| Community Participation → Behavior | 0.623 | [0.565, 0.822] | < .001 |
Community participation also demonstrated a significant indirect effect through self-efficacy (β = 0.182, 95% CI [0.133, 0.281], p < .001). However, the direct effect of community participation on emergency management behavior remained statistically significant (β = 0.441, p < .001). Therefore, self-efficacy partially mediated the relationship between community participation and emergency management behavior. These findings indicate that community participation is associated with behavior both directly and indirectly through enhanced self-efficacy.
3.5. Descriptive Findings
Descriptive analyses were conducted to provide contextual understanding of emergency management behavior and recent emergency experiences among participants. Overall emergency management behavior was high (M = 3.76, SD = 0.39), with 67.9% of participants classified at a high level and 32.1% at a moderate level. The highest-scoring behaviors included preparing medications and health records for hospital transport (M = 3.91), maintaining accessible emergency contact information (M = 3.90), and recognizing emergency warning signs and contacting emergency medical services (EMS 1669) (M = 3.83). Despite the generally favorable behavioral profile, two domains remained comparatively weaker. Family-based emergency assessment and decision-making demonstrated only moderate performance (M = 3.60), and participation in community-based NCD emergency prevention activities showed the lowest score (M = 3.52). These findings are consistent with the structural model, which identified community participation as an important upstream determinant operating through self-efficacy.
Regarding recent emergency experiences, 414 of 1,070 participants with available data (38.7%) reported at least one acute NCD-related emergency during the preceding six months. Among these 414 participants, event types, response times, and first actions were each recorded as mutually exclusive categories. Hypoglycemia was the most frequently reported event (38.9%), followed by chest pain (25.4%), unconsciousness (17.9%), and falls (17.9%). Response was initiated within 15 minutes by 55.0% of participants, whereas 45.0% responded after 15 minutes or longer, and 5.8% took no action at all (Table 5). Taken together, these descriptive findings suggest that although emergency management behavior was generally favorable, important gaps remain in family-level preparedness, community engagement, and timely emergency response. These observations provide practical context for the SEM findings, which highlighted self-efficacy as the central mechanism linking social-contextual resources to emergency management behavior.
| Indicator | n | % |
|---|---|---|
| Emergency management behavior (n = 1,074) | ||
| Overall score (Mean ± SD) | — | 3.76 ± 0.39 |
| High behavior level | 729 | 67.9 |
| Moderate behavior level | 345 | 32.1 |
| Emergency experience, past 6 months (n = 1,070) | ||
| Any emergency event | 414 | 38.7 |
| No emergency event | 656 | 61.3 |
| Type of emergency (among n = 414) | ||
| Hypoglycemic episode | 161 | 38.9 |
| Chest pain / acute coronary syndrome | 105 | 25.4 |
| Unconsciousness | 74 | 17.9 |
| Fall/injury | 74 | 17.9 |
| Response time (among n = 414) | ||
| < 5 minutes | 95 | 22.9 |
| 5-15 minutes | 133 | 32.1 |
| 16-30 minutes | 127 | 30.7 |
| > 30 minutes | 59 | 14.3 |
| First action taken (among n = 414) | ||
| Called EMS (1669) | 118 | 28.5 |
| Drove directly to hospital | 145 | 35.0 |
| Called community health worker | 86 | 20.8 |
| First aid at home | 41 | 9.9 |
| Took no action | 24 | 5.8 |
4. DISCUSSION
4.1. Principal Findings
This study sought to identify the mechanisms through which Health Belief Model (HBM) and Social Cognitive Theory (SCT) constructs explain emergency management behavior among patients with type 2 diabetes mellitus in rural Thailand. The findings demonstrated that emergency management behavior was jointly associated with cognitive and social-contextual factors, with the proposed model explaining 77.6% of the variance in behavior and 75.9% of the variance in self-efficacy.
Three key findings emerged. First, community participation was the strongest direct predictor of emergency management behavior, indicating that engagement in community-based activities and collective health initiatives plays a central role in shaping emergency preparedness and response. Second, self-efficacy demonstrated a significant positive association with behavior and mediated the effects of social-contextual factors on emergency management behavior. Third, among the HBM constructs, only perceived severity retained a significant independent association with behavior after accounting for social support, community participation, and self-efficacy. Together, these findings suggest that emergency management behavior is not explained solely by individual risk perceptions. Rather, behavioral readiness appears to emerge from the interaction between social engagement, efficacy beliefs, and perceptions of disease severity. In particular, the strong associations of community participation and self-efficacy indicate that emergency management behavior is embedded within a broader social context in which individuals develop confidence and preparedness through participation in community networks and health-related activities.
4.2. Community Participation and Self-Efficacy as the Primary Behavioral Pathway
The present study suggests that community participation and self-efficacy constitute the primary pathway through which emergency management behavior is developed among individuals with chronic diseases [19]. Community participation emerged as the strongest predictor of behavior and demonstrated a substantial positive association with self-efficacy. In turn, self-efficacy was independently associated with emergency management behavior and partially mediated the relationship between community participation and behavior. These findings are consistent with previous research indicating that community-based engagement enhances self-management and behavioral outcomes among individuals with chronic conditions. Similarly, Cameron et al. (2018) [20] reported that social identification within health-related groups promotes positive health outcomes through self-efficacy pathways. From the perspective of Social Cognitive Theory, participation in community activities may provide opportunities for observational learning, social reinforcement, and confidence building, thereby strengthening efficacy beliefs and facilitating adaptive behavioral responses [21]. Notably, the direct effect of community participation remained significant after accounting for self-efficacy, indicating partial mediation. This finding suggests that community participation is associated with emergency management behavior not only through enhanced self-efficacy but also through additional mechanisms such as social connectedness, information exchange, and collective problem-solving. Consistent with Vassilev et al. (2014) [22], social networks may facilitate chronic disease management through collective efficacy, resource sharing, and access to practical support. Together, these findings highlight community participation and self-efficacy as complementary targets for interventions designed to strengthen NCD emergency preparedness in rural communities.
4.3. Why Perceived Severity Remained Significant While other HBM Constructs did not
An interesting finding was that perceived severity was the only Health Belief Model construct that remained significantly associated with emergency management behavior after adjustment for social-contextual factors and self-efficacy. In contrast, perceived susceptibility, perceived benefits, and perceived barriers were not significant predictors in the final model. One possible explanation is that emergency situations may place greater emphasis on individuals’ perceptions of the seriousness and consequences of symptoms than on evaluations of benefits, barriers, or personal susceptibility. In acute situations, recognizing the potential severity of an event may act as an immediate cue for action, prompting timely help-seeking and emergency response behaviors. This interpretation is broadly consistent with previous Health Belief Model research. More recent evidence from Marsim et al. (2021) [23] demonstrated that strong perceived severity increased the likelihood of implementing tertiary prevention behaviors in type 2 diabetes patients by 4.69 times (aOR = 4.69; 95% CI = 1.92 to 11.47). Similarly, Daniel and Messer (2002) [24] found that perceived severity was associated with diabetes-related health management outcomes. The present findings extend this evidence by suggesting that perceptions of severity may remain particularly relevant in the context of NCD emergency management. Taken together, the findings indicate that while cognitive perceptions remain important, emergency management behavior is more comprehensively explained when perceptions of severity are considered alongside social-contextual influences and self-efficacy. This interpretation is supported by the stronger effects observed for community participation and self-efficacy in the final structural model.
4.4. Practical Implications
The findings have several implications for the design of NCD emergency preparedness interventions in rural communities. First, intervention strategies should extend beyond the provision of health information alone and focus on strengthening self-efficacy, as confidence in recognizing and responding to emergencies was significantly associated with emergency management behavior. This recommendation is supported by previous research demonstrating that self-efficacy is an important determinant of emergency preparedness behaviors [25]. Second, the strong association between community participation and behavior suggests that community-based approaches may represent an effective strategy for supporting emergency preparedness. Engagement in local health activities, village health volunteer programs, and community support networks may provide opportunities for experiential learning, information sharing, and collective problem-solving. This interpretation is consistent with evidence highlighting community engagement as a key component of resilience and preparedness in rural settings [26]. Collectively, these findings support the development of integrated interventions that combine community engagement and self-efficacy enhancement to strengthen emergency management behavior among individuals with chronic diseases.
4.5. Strengths and Limitations
This study has several strengths. First, it was guided by an integrated theoretical framework combining the Health Belief Model and Social Cognitive Theory, enabling simultaneous examination of cognitive, social-contextual, and behavioral mechanisms underlying NCD emergency management. Second, the large community-based sample provided adequate statistical power for structural equation modeling. Third, the use of confirmatory factor analysis, structural equation modeling, and bootstrap mediation analysis allowed rigorous evaluation of both direct and indirect pathways. Several limitations should also be acknowledged. First, the cross-sectional design precludes causal inference and limits conclusions regarding temporal relationships among variables. Second, the study relied on interviewer-administered self-report measures and may therefore be subject to recall and social desirability biases. Third, participants were recruited from rural communities in Thailand, which may limit the generalizability of the findings to urban populations or other sociocultural settings. In addition, social support and community participation demonstrated substantial overlap, as indicated by high latent correlations and HTMT values. Although retained as theoretically distinct constructs, some degree of conceptual redundancy cannot be excluded. Because the two constructs share substantial variance, their separate direct effects are estimated with less precision than would be the case for fully distinct predictors, and the non-significant direct effect of social support should therefore be interpreted with corresponding caution. Relatedly, the internal consistency coefficients observed here were high (Cronbach’s α = 0.934-0.975; McDonald’s ω = 0.935-0.975), exceeding the range commonly reported for multi-item health behavior scales. Coefficients of this magnitude may reflect item redundancy, as items within each subscale were written to capture closely related facets of a single construct, and the interviewer-administered format may have further increased response consistency. Although all constructs satisfied conventional reliability and validity criteria, shorter item sets might achieve comparable measurement precision, and future applications of this instrument could examine whether the subscales can be abbreviated without loss of information. Future studies using refined measures or longitudinal designs would help establish whether the two domains are better represented as distinct constructs or as facets of a broader social-contextual dimension.
CONCLUSION
This study provides evidence that emergency management behavior among individuals with chronic diseases is associated with both cognitive and social-contextual factors. Community participation emerged as the strongest predictor of behavior, while self-efficacy functioned as an important behavioral mechanism linking social-contextual resources to emergency management behavior. Among the Health Belief Model constructs, only perceived severity retained a significant independent association with behavior in the final model. The findings suggest that effective NCD emergency preparedness interventions should extend beyond risk awareness alone and incorporate strategies that strengthen community engagement and self-efficacy. Integrating these components into community-based health programs may enhance emergency response capacity and support preparedness among individuals living with chronic diseases in rural settings.
AUTHORS’ CONTRIBUTIONS
The authors confirm their contributions to the paper as follows: study conception and design: CS; data collection: SA, CS; analysis and interpretation of results: CS, SA; draft manuscript: CS. All authors reviewed the results and approved the final version of the manuscript.
List of Abbreviations
| 1669 | = Thailand emergency medical service hotline |
| AVE | = Average Variance Extracted |
| CFA | = Confirmatory Factor Analysis |
| CFI | = Comparative Fit Index |
| CI | = Confidence interval |
| EMS | = Emergency Medical Services |
| HBM | = Health Belief Model |
| HTMT | = Heterotrait-Monotrait ratio of correlations |
| IOC | = Item-Objective Congruence |
| NCDs | = Non-communicable diseases |
| p-value | = Probability value |
| R2 | = Coefficient of determination |
| RMSEA | = Root Mean Square Error of Approximation |
| SCT | = Social Cognitive Theory |
| SEM | = Structural Equation Modeling |
| SRMR | = Standardized Root Mean Square Residual |
| T2DM | = Type 2 Diabetes Mellitus |
| TLI | = Tucker-Lewis Index |
ETHICS APPROVAL AND CONSENT TO PARTICIPATE
This study was approved by the Human Research Ethics Committee of Sisaket Province (No. SPPH 2026-034, dated 18 February 2026).
HUMAN AND ANIMAL RIGHTS
No animals were used in this research. All procedures performed in studies involving human participants were in accordance with the ethical standards of institutional and/or research committees and with the 1975 Declaration of Helsinki, as revised in 2013.
CONSENT FOR PUBLICATION
Informed consent was obtained from all participants prior to data collection.
AVAILABILITY OF DATA AND MATERIAL
Available from the corresponding author upon reasonable request, subject to ethics committee approval (SPPH 2026-034).
ACKNOWLEDGEMENTS
The authors thank all participants, the Sisaket Provincial Public Health Office, District Public Health Offices of all 22 districts, primary care unit staff, and village health volunteers for their invaluable support. This study was supported by the SCPHUB Research Fund, Fiscal Year 2025, Sirindhorn College of Public Health, Ubon Ratchathani Province.

